Deterministic rules
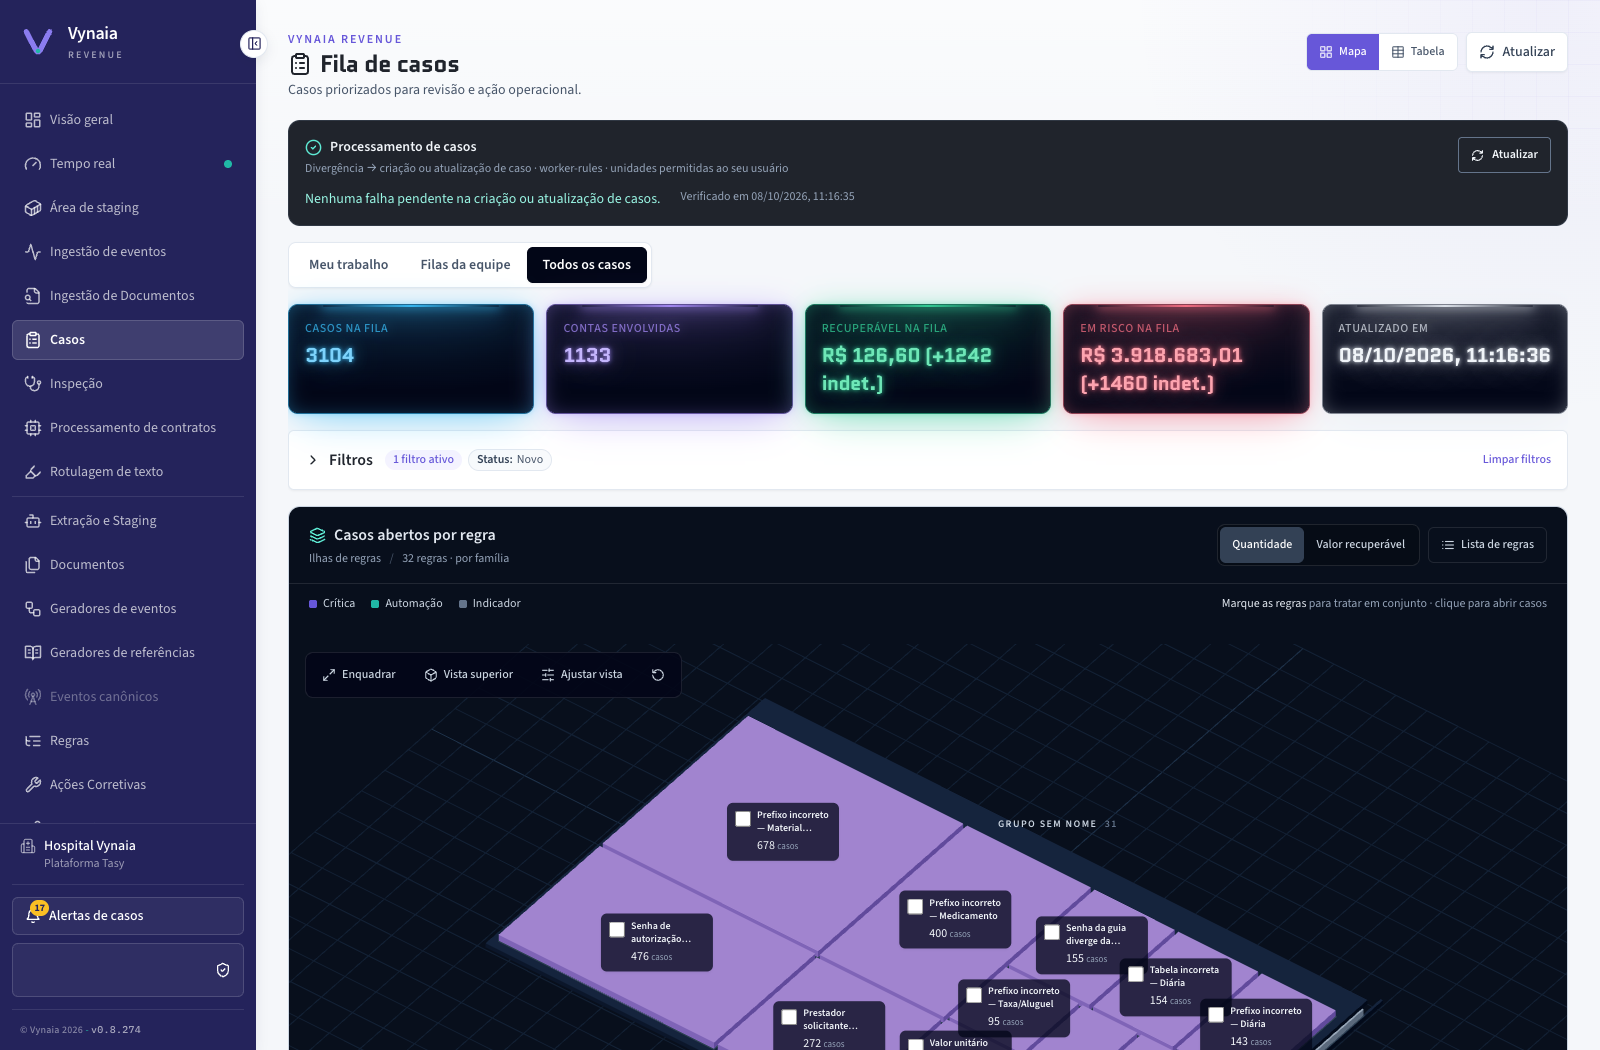
- Duplicate daily rate
- Missing authorization password
- Claim password differs from the authorization
- Password validity before billing start
- Claim number mismatch
- Claim number repeated on another account
- Requesting provider differs from the performing provider
- Wrong table — Medication
- Invalid quantity — Daily rate
- Zero unit price
- Missing admission claim
- Item date after the end of the partial bill
Contracts read by AI
- Charged price vs negotiated price
- Claim price vs contract table
- Contractual submission deadline
- Daily-rate count vs contract convention
- Claim daily rates vs contract convention
- Urgency uplift vs contract clause
- Urgency notification deadline
- Accommodation uplift vs plan entitlement
- Rates and percentages vs contract terms
- Claim uplift vs contract terms
Vynaia Revenue · Hospital revenue intelligence and assurance
Protect every source of hospital revenue.
Vynaia connects clinical, operational, billing, and payer events to identify missing charges, inconsistencies, authorization risks, and potential denials before they become financial losses.
Before the claim reaches the payer. Alongside your hospital information system, not in its place.
Evidence
Prioritized discrepancy
Controlled action
- 1Clinical events
- 2Billing account
- 3Claims and authorizations
- 4Payer contracts
The problem
Where hospital revenue is lost.
Hospitals lose revenue when what happens in care does not reach the account and the claim sent to the payer completely and consistently.
- 01What happened in care.
- 02What was recorded on the account and the claim.
- 03What the payer will refuse.
- 04What Vynaia points out before submission.
- RuleDuplicate daily rate
- RuleClaim password differs from the authorization
- Contract · AICharged price above the negotiated price
Prioritized discrepancy · before submission
Care
What happened to the patient
Account and claim
What was recorded and billed
Payer
What is actually paid
Missing charge
An administered item, procedure, or daily rate that never reaches the account is never billed.
Denial
Incomplete or inconsistent data on the claim leads the payer to refuse payment.
Late correction
What is only noticed after submission becomes an appeal, rework, and a delayed payment.
Vynaia Revenue exists to find these problems in the data before the claim reaches the payer.
Fewer losses.Fewer denials.More predictability.
From care to billing, every event matters.
The product
Real screens from Vynaia Revenue.
Captured from the application with demonstration data. The interface is in Brazilian Portuguese.
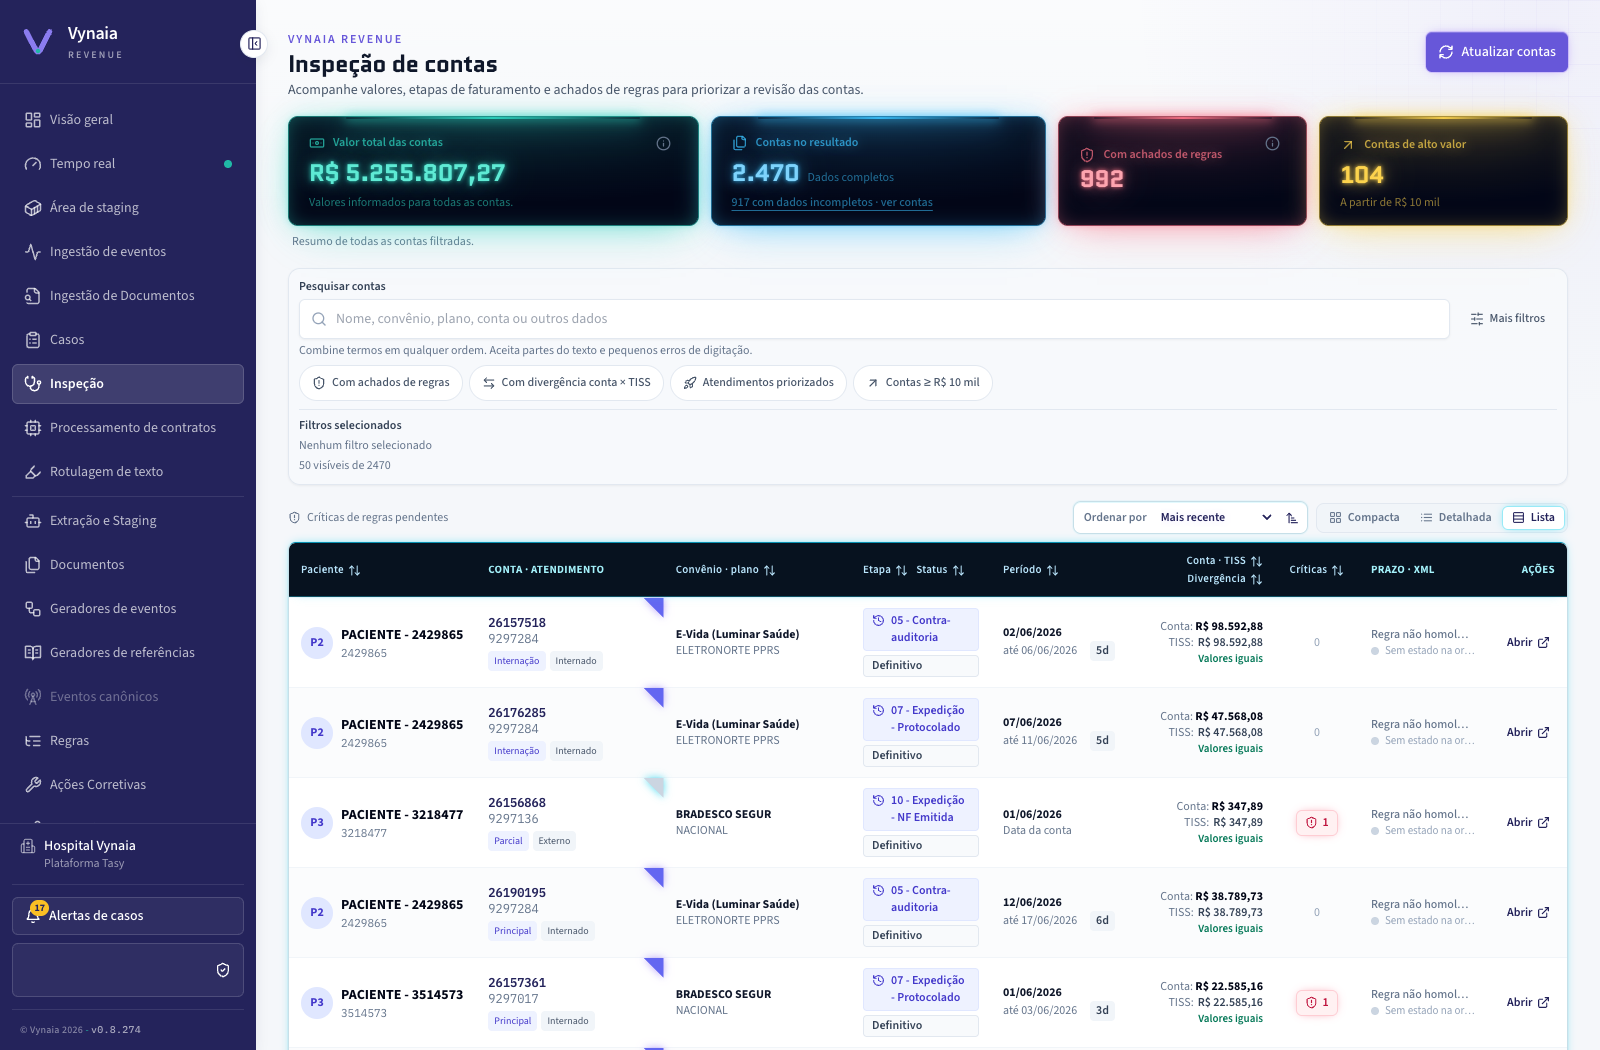
See which accounts are at risk of loss before submission.
The inspection list brings together the account value, the claim (TISS) value, the billing stage, pending rule findings, and the XML deadline, sortable by account and encounter.
How it works
Correct before submission, not after the denial.
A governed path connects source records to the people who decide.
- 01
Connect
A configured local agent collects the eligible data from the hospital system.
- 02
Organize
Staging and canonical events preserve the source context of every record.
- 03
Review
Account views, approved rules, and contract checks bring the evidence together.
- 04
Act
Teams decide, follow cases, and authorize the corrections the policy allows.
Collection scope, available checks, and corrections depend on the approved configuration.
Use cases
Where the loss happens, and what Vynaia points out.
Every finding requires the applicable rule or check and sufficient evidence. Nothing is flagged without a trail back to the source.
Missing charges
Administered items, procedures, and daily rates recorded in care that do not appear on the account.
Loss: revenue that is never billed.
Account versus claim differences
Values, quantities, and identifiers that differ between the hospital account and the submitted claim (TISS guide).
Loss: a denial caused by a discrepancy on the claim.
Authorizations and passwords
Missing or expired authorization passwords and quantities above the authorized amount, before submission.
Loss: a claim refused for a missing or expired authorization.
Contract prices and terms
Price tables and clauses read from payer contracts, available to the configured contract checks.
Loss: a charge outside the negotiated value.
Clinical and documentary evidence
Clinical history, records, and documents next to every questioned charge.
Loss: a charge without support when the payer questions it.
Corrections with control
Approved corrective actions, executed according to policy and recorded in the audit trail.
Loss: a late correction, with an appeal and rework.
Architecture and integration
Alongside your HIS, not in its place.
A local agent collects only the eligible data from the hospital system. The platform organizes and reviews it and returns decisions. The HIS remains the source of record.
Local integration agent
Extraction is configured, validated, and published with a defined scope before it runs.
Role-based access control
Permissions and hospital-unit scope define who can read, decide, and operate.
Audit logging
Decisions, approvals, and actions are recorded with a reference to their source.
Configurable retention
Retention policies apply to operational data and evidence.
Governance
Confidence starts with a traceable decision.
Rules, contracts, and actions are reviewed before they take effect. Every decision keeps who decided and on what basis.
Review before activation
Versioned configurations and approval workflows keep changes deliberate.
Access with a defined scope
Permissions and hospital-unit scope govern who can read, decide, and operate.
A history you can follow
Source references, case evidence, and audit records connect actions to their context.
- 1
Evidence
The source record and the clinical and billing context
- 2
Review
Who reviewed it, and which rule or contract version applied
- 3
Approval
The approver, and what the policy required
- 4
Action
The action taken and its audit entry
Vynaia uses AI and configurable rules to identify patterns, classify discrepancies, organize evidence, and recommend actions. Execution remains governed by policy, confidence, permissions, and audit requirements.
Measurement
Estimated impact is not recovered revenue.
Financial measures stay separate, and each one has its own evidence.
No customer results or performance claims are published without methodology and approval.
Estimated impact
Potential value of open findings, before any confirmation.
Confirmed value
Contribution verified at the source after the correction.
Recovered revenue
Receipt recorded by the payer, where reconciliation is available.
Products
One platform, extended by capability.
Vynaia Revenue is the first product. The product architecture plans extensions under the same brand.
- In initial deployment
Vynaia Revenue
Hospital revenue intelligence and assurance.
- Planned
Vynaia Connect
Integration with hospital systems, payer systems, and external networks.
- Planned
Vynaia Clinical
Clinical intelligence and workflow support.
- Planned
Vynaia Authorize
Eligibility, authorization, and payer communication.
- Planned
Vynaia Insights
Analytics, executive intelligence, and operational indicators.
Questions
Before we talk.
Which losses does Vynaia help prevent?
Mainly three: charges that never reach the account, denials caused by incomplete or inconsistent data on the claim, and corrections made only after submission, which become appeals and rework. Vynaia points out these problems with evidence before the claim reaches the payer.
Does Vynaia replace our hospital system?
No. Vynaia works alongside the HIS, bringing the collected billing and clinical context into inspection, governed checks, and case workflows. The hospital system remains the source of its operational records.
Can our team define its own billing checks?
Authorized users can author configurable rules, test known account examples, and submit versions for review. What a rule can evaluate depends on the available source facts and approved field mappings.
Are corrections automatic?
Only when a supported integration, an activated action, and an approved policy allow it. Human review and authorization are part of the workflow; autonomous correction is not a default.
What about contracts, documents, and AI?
These workflows depend on enabled modules, source coverage, processing profiles, and approved model configuration. AI suggestions are distinguished from confirmed findings and recorded financial outcomes.
Are these real product screenshots?
Yes. They were captured from the application in a demonstration environment with fictional data. The signed-in user identity is covered. They are not customer results.
Next step
Let’s find where your hospital’s revenue is being lost.
Tell us how your billing team works today. We will show where the platform fits and what it needs from your systems.
Or write to us at contato@vynaia.com.br